Army Nurse Corps Officer (AN)
An Army nursing career may begin on a hospital ward, then move into trauma care, deployment with a combat brigade or leadership of a team in the field. Along the way, the Army offers funded entry routes, opportunities for graduate education and retirement benefits.
The Nurse Corps is the Army Medical Department (AMEDD) officer branch for registered nurses, working alongside the Medical Corps, Medical Service Corps and Specialist Corps. New BSN graduates can apply without years of ward experience because the Army provides a structured training path.
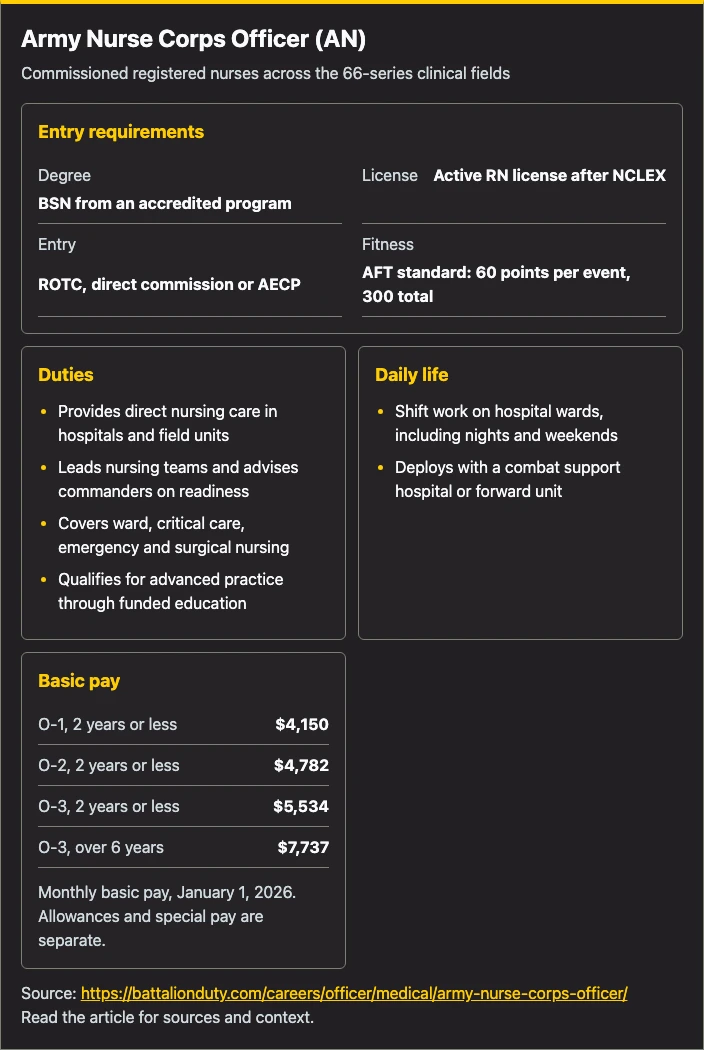
Entry requirements
- Degree
- BSN from an accredited program
- License
- Active RN license after NCLEX
- Entry
- ROTC, direct commission or AECP
- Fitness
- AFT standard: 60 points per event, 300 total
Duties
- Provides direct nursing care in hospitals and field units
- Leads nursing teams and advises commanders on readiness
- Covers ward, critical care, emergency and surgical nursing
- Qualifies for advanced practice through funded education
Daily life
- Shift work on hospital wards, including nights and weekends
- Deploys with a combat support hospital or forward unit
Basic pay
- O-1, 2 years or less
- $4,150
- O-2, 2 years or less
- $4,782
- O-3, 2 years or less
- $5,534
- O-3, over 6 years
- $7,737
Monthly basic pay, January 1, 2026. Allowances and special pay are separate.
Source: https://battalionduty.com/careers/officer/medical/army-nurse-corps-officer/
Read the article for sources and context.
On this page
Job Role and Responsibilities
Army Nurse Corps officers are commissioned registered nurses who provide direct care, lead teams and advise commanders on nursing readiness in hospitals and field units. Their areas of concentration use 66-series codes to identify clinical fields. The branch covers ward care, critical care, emergency care, surgery, mental health, public health and advanced practice.
Command and Leadership Scope
A new Nurse Corps officer leads a small team on a ward, in a clinic or in a field unit. A 66H nurse, for example, may supervise 68C Practical Nursing Specialists on a ward, set care standards and report to a department chief.
At the Major and Lieutenant Colonel levels, officers may become nursing leaders, department chiefs or unit commanders. Senior officers can serve as a hospital’s Chief Nurse, overseeing nursing standards, credentials, staffing and care quality across the facility.
The branch offers battalion-level and higher command positions, mostly within medical units. Nurse Corps officers may pursue clinical ward leadership, a command track or a combination of both, extending their opportunities beyond the clinic.
Specific Roles and Designations
New graduate nurses commonly begin in 66H, while applicants already qualified in a specialty may enter through that specialty’s accession route. Additional education can qualify serving officers for other AOCs:
| AOC Code | Specialty | Minimum Qualification |
|---|---|---|
| 66H | Medical-Surgical Nurse | BSN + RN license (entry-level AOC) |
| 66S | Critical Care Nurse | BSN + RN + critical care training |
| 66T | Emergency Nurse | BSN + RN + emergency nursing training |
| 66E | Perioperative Nurse | BSN + RN + perioperative nursing training |
| 66G | Obstetric-Gynecologic Nurse | BSN + RN + OB/GYN nursing training |
| 66B | Army Public Health Nurse | BSN + RN + public health coursework |
| 66C | Psychiatric/Behavioral Health Nurse | BSN + RN + behavioral health nursing training |
| 66P | Family Nurse Practitioner | Graduate degree + FNP certification (advanced practice) |
| 66R | Psychiatric/Behavioral Health Nurse Practitioner | Graduate degree + PMHNP certification (advanced practice) |
| 66F | Nurse Anesthetist (CRNA) | Master’s or DNP + CRNA certification |
| 66W | Certified Nurse Midwife | Graduate degree + CNM certification |
| 66N | Operational Nurse (duty AOC only) | Senior officer staff or administrative billet |
Skill Identifiers mark additional credentials or degrees attached to an AOC. In mental health, 66C identifies registered nurses and 66R nurse practitioners. Graduate-level advanced practice AOCs include CRNAs, nurse practitioners and nurse midwives, with Army-funded education available for those paths.
Four of these AOCs have their own guides. Read the critical care nurse, emergency nurse, perioperative nurse and nurse anesthetist pages for the detail on each.
Mission Contribution
Army nursing supports force readiness as well as healthcare. A brigade entering high-intensity combat needs nurse teams capable of managing mass casualties, providing critical care at Role 2 or Role 3 facilities and maintaining coverage for weeks. Nurse Corps officers provide that capability.
In garrison, Nurse Corps officers run programs at Army hospitals serving more than a million soldiers, retirees and family members. In the field, they staff forward surgical teams, combat support hospitals and joint facilities with partner forces. Their care affects recovery time and soldiers’ return to duty.
Technology, Equipment, and Systems
Officers document care in Military Health System Genesis, the DoD electronic health record (EHR). Field nurses rely on portable monitors, field-grade critical care equipment and rapid testing tools built for austere sites, while senior leaders use software to track staffing and quality. Telehealth connects forward nurses with specialists at home stations.

Salary and Benefits
Base Pay (2026)
Nurse Corps officers can commission at O-1 through ROTC or enter through direct commission after completing a BSN. Prior service or graduate education may raise the entry grade. The pay figures below come from DFAS 2026 Military Pay Charts.
| Rank | Grade | Years of Service | Monthly Base Pay |
|---|---|---|---|
| Second Lieutenant | O-1 | Less than 2 | $4,150 |
| Second Lieutenant | O-1 | 2 years | $4,320 |
| First Lieutenant | O-2 | 2 years | $5,446 |
| First Lieutenant | O-2 | 4 years | $6,485 |
| Captain | O-3 | Less than 2 | $5,534 |
| Captain | O-3 | 4 years | $7,383 |
| Captain | O-3 | 8 years | $8,126 |
| Major | O-4 | Less than 2 | $6,295 |
| Major | O-4 | 8 years | $8,816 |
| Lieutenant Colonel | O-5 | 16 years | $11,391 |
Nurse Corps Special Pays
Base pay is only part of the total. Depending on specialty and eligibility, officers may qualify for:
- Accession Bonus (AB): an incentive for eligible accessions, tied to the current offer and an additional service agreement.
- Retention Bonus (RB): a payment for eligible nurses who accept a defined service commitment. Amounts, payment timing and obligations follow the agreement.
- Incentive Pay (IP): additional pay for qualifying specialties under current program rules, including rules governing concurrent receipt with a retention bonus.
- Nurse anesthesia (66F): advanced-practice qualifications can carry distinct special-pay eligibility. Ask a recruiter for the current offer and required obligation.
Additional Benefits
Officers receive Basic Allowance for Subsistence (BAS) of $328.48 a month and Basic Allowance for Housing (BAH) based on post, grade and family status. An O-3 at Fort Sam Houston gets $2,007 a month without family or $2,127 with family. Both allowances are tax-free, and BAH is higher at more costly posts.
Active-duty nurses receive TRICARE coverage, and eligible family members can enroll in the available plans. Family costs depend on the plan and care received; check current TRICARE costs and fees rather than assume every service is free. Officers also earn 30 days of paid leave per year.
Under the Blended Retirement System (BRS), officers who reach 20 years earn a pension equal to 40% of their high-36 base pay. The Army begins contributing 1% of base pay to the Thrift Savings Plan (TSP) after 60 days and adds matching contributions of up to 4% after two years. Officers must contribute 5% themselves to receive the full match.
Work-Life Balance
In garrison, nurses work scheduled hospital shifts, take call and participate in field drills, while nurse leaders handle additional staff responsibilities. Exercises, deployments and mass casualty events disrupt that routine and can require long shifts without a fixed end.
Qualifications and Eligibility
Commissioning Sources
ROTC, direct commission and AECP provide routes into the Nurse Corps. Once commissioned, selected officers can pursue advanced practice education through LTHET.
ROTC (with Nurse Summer Training Program): Nursing students can join ROTC while finishing a BSN. Between junior and senior year, the four-week Nurse Summer Training Program (NSTP) places cadets at an Army hospital, at participating Army hospitals in the United States or overseas They log at least 120 clinical hours under an Army nurse’s supervision. After completing school and passing the NCLEX, they commission as Second Lieutenants.
Direct Commission: Licensed RNs with a BSN or higher can enter without first completing ROTC or OCS, making this the most common route for working nurses. They attend the AMEDD Direct Commission Course for introductory officer training, followed by BOLC.
AECP (Army Enlisted Commissioning Program): Enlisted soldiers at E-4 or above can apply after at least 24 months of service. The competitive, merit-based program lets them finish a BSN on full pay and benefits before commissioning into the Nurse Corps. Current application cycles are posted at recruiting.army.mil/aecp.
Commissioning Requirements
| Path | Degree Required | Licensure | Age Limit | ADSO |
|---|---|---|---|---|
| ROTC | BSN (in-progress) | NCLEX-RN required before active duty | Under 31 at commissioning (waiverable) | 4 years (scholarship); 3 years (non-scholarship) |
| Direct Commission | BSN minimum (MSN/DNP for advanced practice) | Active, unrestricted RN license required | Under 47 at commissioning (varies) | 3-4 years |
| AECP | Earn BSN on active duty | NCLEX-RN required before commissioning | Varies by program | 4 years |
Every path requires U.S. citizenship, a passing military physical and eligibility for a Secret clearance. Officers must also hold a clean state RN license before reporting for active duty in a clinical position.
Test Requirements
Nurse Corps entry requires the appropriate nursing qualifications and licensure. The NCLEX-RN is a licensing examination, not an enlisted entrance test; applicants should follow the Nurse Corps accession route rather than assume that a general OCS or ASVAB requirement applies to every nurse.
Branch Selection and Assignment
ROTC nursing cadets seek Nurse Corps assignments through their commissioning program, while direct-commission applicants work with AMEDD recruiting for their specialty. Officers rank assignment preferences through the applicable Request for Assignment (RFA) process, and Human Resources Command makes assignments according to qualifications and Army needs.
Upon Commissioning
ROTC and AECP officers commission at O-1, while direct commission officers usually enter at O-1 or O-2 depending on prior service. The combined obligation is eight years across active duty and reserve or standby service. A four-year active-duty period counts toward that total, with the remaining obligation served in reserve status.

Work Environment
Setting and Schedule
Hospital assignments range from major medical centers, such as Brooke Army Medical Center and Walter Reed, to smaller facilities. Nurse Corps officers work across wards, critical care units, emergency departments, operating rooms and clinics, with assignments depending on their specialty.
Field assignments differ from hospital duty. Officers on forward surgical teams participate in field exercises using deployable equipment, and their operating sites may range from permanent buildings to tents with limited diagnostic tools.
Nurse Corps officers also serve as medical planners and force health advisers on division and corps staffs. These positions involve mostly office work but can become demanding during exercises and deployments.
Leadership and the NCO Dynamic
The senior enlisted partner is often a 68C Practical Nursing Specialist serving as a sergeant or staff sergeant, although a medical platoon sergeant may fill the role. In hospitals, experienced NCOs coordinate daily floor operations, medication rounds, patient movements and supplies. Officers set nursing standards, make clinical decisions and oversee credentials and staff evaluations.
Nurse officers work with enlisted clinical staff, including 68C practical nursing specialists, as members of a patient-care team. Effective collaboration needs clear responsibilities and respect for both clinical expertise and military authority.
Staff vs. Command Roles
Most early-career assignments involve ward care, with staff opportunities increasing at Major as officers move into planning, director and headquarters positions. The command route includes medical company command and can lead to Chief Nurse billets. Officers interested in command should pursue field assignments and express that goal early.
Retention and Job Satisfaction
Retaining nurses remains a challenge because civilian nursing, particularly travel nursing, can pay more than Army base pay at O-2 and O-3. Specialty pay and benefits such as housing, healthcare, retirement and funded graduate study help narrow the gap. Nurses who stay often value varied ward assignments, early leadership and the field mission.
Training and Skill Development
Pre-Commissioning Training
ROTC nursing cadets complete their commissioning coursework and may take part in the Nurse Summer Training Program to gain experience in Army hospitals. Direct-commission candidates attend the required AMEDD officer training, including military fundamentals, fitness and field leadership. The exact sequence follows the current accession instructions.
Basic Officer Leader Course (BOLC)
AMEDD BOLC at the Medical Center of Excellence (MEDCoE), Fort Sam Houston, develops the military skills Nurse Corps officers need for their assignments. The course sequence and duration depend on component, prior training and current accession instructions.
The current MEDCoE course instructions and issued orders establish the required training sequence. Check those instructions before making travel or career plans around a generic BOLC duration.
Clinical Nurse Transition Program (CNTP)
New graduate nurses entering the medical-surgical pathway complete the Clinical Nurse Transition Program (CNTP) to develop clinical practice in the Army setting. The program uses supervised patient care and instruction over approximately six months; the assigned site’s current training plan controls its clinical hours and schedule.
CNTP prepares newly commissioned nurses for solo ward work by covering patient checks in the Army setting, charting in Military Health System Genesis and Army nursing standards. Completing the program provides a base for later AOC courses.
Professional Military Education (PME)
| Course | Typical Timing | Location | Duration |
|---|---|---|---|
| Captain’s Career Course (CCC) | O-3, 7-9 years in service | Fort Sam Houston, TX | 8-12 weeks |
| Intermediate Level Education (ILE/CGSC) | O-4, 14-16 years | Fort Leavenworth, KS | 10-12 months |
| Senior Service College (War College) | O-5/O-6 | Various | 10-12 months |
CCC focuses on nursing leadership, healthcare operations and field nursing. ILE is required for advancement above O-4 and for command, while competitive selection for Senior Service College identifies officers on a senior leadership track.
Specialty AOC Courses and Advanced Education
After initial clinical development, nurses may pursue specialty AOC courses subject to each course’s entry requirements. Critical care, emergency, perioperative and nurse anesthesia pathways have separate guides; additional fields include:
- Psychiatric/Behavioral Health Nursing (66C / 66R): mental health nursing training for the 66C registered-nurse code; the 66R practitioner code requires graduate-level psychiatric education and advanced-practice credentials
- Public Health Nursing (66B): Principles of Military Preventive Medicine course
- Obstetric-Gynecologic Nursing (66G): OB/GYN nurse course
Through Long-Term Health Education and Training (LTHET), selected serving officers can pursue nurse anesthesia, family nurse practitioner, psychiatric nurse practitioner or nurse-midwifery education while receiving active-duty pay and benefits. Program length, funding and the additional service obligation depend on the selected course and agreement.
Career Progression and Advancement
Career Timeline
| Rank | Grade | Typical Time in Service | Key Assignment |
|---|---|---|---|
| Second Lieutenant | O-1 | 0-18 months | BOLC, CNTP, first MTF ward assignment |
| First Lieutenant | O-2 | 18 months - 4 years | Ward nurse, specialty AOC course eligible, RFA process |
| Captain | O-3 | 4-10 years | Charge nurse, department OIC, CCC, specialty AOC assignment |
| Major | O-4 | 10-16 years | Nurse manager, department chief, battalion staff, LTHET eligible |
| Lieutenant Colonel | O-5 | 16-22 years | Medical unit command, MTF Chief Nurse, ILE |
| Colonel | O-6 | 22-30 years | MTF Chief Nurse (large MTF), MEDCOM staff, senior advisor |
Promotion from O-1 through O-3 generally follows time in grade and satisfactory evaluations, while O-4 selection is more competitive and board-driven, with rates similar to other medical branches. Later boards consider performance records, schooling and command experience.
Promotion Factors
Strong promotion records demonstrate increasing nursing leadership, AOC proficiency and field experience. Officers whose careers remain entirely on wards without field or staff assignments may struggle to advance beyond O-4. Charge nurse and department positions, timely AOC training and field tours all strengthen the record.
Branching Out and Functional Areas
Officers interested in health system management should confirm the qualifications and transfer rules for Medical Service Corps health-services specialties rather than assume an automatic “FA 70” route from nursing. Broadening opportunities can also include ROTC instruction, recruiting, fellowships and joint medical staff assignments, subject to selection and available billets.
Building a competitive record means volunteering early for field exercises and tours, completing AOC courses promptly and treating education as part of career planning. Chief Nurse positions favor officers with ward, field and leadership experience.
Physical Demands and Medical Evaluations
Nurse Corps officers take the Army Fitness Test, which replaced the ACFT on June 1, 2025. Because nursing is not a designated combat field, the general passing standard applies: 300 points overall, with at least 60 per event under age- and sex-based scoring.
Army Fitness Test (AFT)
The AFT has five events, each worth up to 100 points, for a maximum total of 500.
| Event | Abbreviation | Description |
|---|---|---|
| 3-Rep Max Deadlift | MDL | Maximum weight for 3 repetitions |
| Hand Release Push-Up | HRP | Full arm extension at bottom of each rep |
| Sprint-Drag-Carry | SDC | 5-lane, 50-meter shuttle with drag and carry |
| Plank | PLK | Timed hold in plank position |
| Two-Mile Run | 2MR | Timed two-mile run |
Source: Army Fitness Test
Branch-Specific Medical Requirements
Officers must maintain an unrestricted RN license and any additional credentials required for their role. A lapse or revocation can affect clinical privileges and specialty eligibility. Additional physical examinations depend on the duties and assignment rather than the nursing title alone.
Deployment and Duty Stations
Deployment Details
Officers assigned to deployable medical units follow that unit’s operational requirements. Deployment length and timing vary by mission and orders, so a generic nine-to-twelve-month example should not be treated as an individual schedule.
Nurses in high-demand specialties deploy more frequently, sometimes to fill individual critical care, surgical or emergency nursing slots when theater demand rises. These tours can last three to six months and may have less notice than unit deployments. Nurse anesthetists deploy particularly often because of staffing shortages.
Hospital-based officers at U.S. posts deploy less frequently but may still be assigned disaster relief, joint exercises or theater support missions.
Duty Station Options
Nursing positions are available at a range of medical facilities. Examples include:
- Brooke Army Medical Center: Fort Sam Houston, Texas (largest AMEDD installation)
- Walter Reed National Military Medical Center: Bethesda/D.C. area
- Tripler Army Medical Center: Honolulu, Hawaii
- Madigan Army Medical Center: Joint Base Lewis-McChord, Washington
- Womack Army Medical Center: Fort Bragg, North Carolina
- Blanchfield Army Community Hospital: Fort Campbell, Kentucky
- Ireland Army Health Clinic: Fort Knox, Kentucky
- Winn Army Community Hospital: Fort Stewart, Georgia
Officers submit ranked preferences through the RFA process, but Human Resources Command balances those preferences against qualifications and Army needs. Later assignments follow the same principle: an available nursing billet does not guarantee a particular posting.
Risk, Safety, and Legal Considerations
Job Hazards
Field nursing exposes officers to risks faced by the soldiers they treat, including blasts, small-arms threats during movement and care in austere conditions. Forward surgical teams and combat support hospitals may handle mass casualties under fire, with limited supplies and no nearby civilian trauma center.
Clinical risks include bloodborne pathogens, lifting-related strains and the mental burden of caring for injured patients. Mental health nurses and psychiatric nurse practitioners may also experience secondary trauma through their work.
Legal and Command Responsibility
Nurse Corps officers have obligations under both the UCMJ and their state nursing boards. A clinical error may lead to a malpractice claim, licensing investigation or military action. For covered claims involving care within assigned duties, 10 U.S.C. § 1089 generally makes the remedy against the United States exclusive of a personal civil action against the clinician. Negligence does not by itself remove that protection. Military discipline and licensing action are separate, and work outside assigned duties requires separate legal analysis.
Nurse officers are accountable for their assigned leadership responsibilities, including patient welfare, professional conduct and compliance with equal opportunity standards and Army Values. Officers appointed to command also carry the authority and responsibilities of that command.
Risk Management
Nurse leaders include risk management in field planning and patient-safety work. A field plan must account for patient load, blood supply, medication storage and evacuation timing; hospital work also requires the applicable clinical and accreditation procedures.
Impact on Family and Personal Life
Family Considerations
Officers typically move every two to three years, consistent with Army-wide assignment cycles. Over a 20-year career, these moves can disrupt a spouse’s employment, children’s schooling and community ties. Army Community Service and Family Readiness Groups provide relocation support, although quality varies by post.
Dual-military couples face additional assignment constraints and can request joint domicile, although approval depends on available billets at the same post. Larger medical installations can improve the chances of a compatible placement.
Nurse license rules matter for civil nurse spouses who move states. The Nurse Licensure Compact (NLC) now covers most states. Not every state takes part.
Deployment Impact
Extended deployments can place substantial demands on families. Eligible health coverage, childcare and family-support programs may help, but availability and individual circumstances matter. High-demand assignments can also make the timing of separation difficult to predict.
Dual-nurse couples may encounter conflicting assignments, so early planning matters. Human Resources Command operates joint-domicile programs without guaranteed results, and families seeking more stability often favor hospital-heavy posts with more nursing billets and a lower operational tempo.
Reserve and National Guard
Component Availability
The Nurse Corps serves in both the Army Reserve and the Army National Guard. Reserve nurses fill positions in hospital units and other medical organizations. Guard nurses serve in state medical units that may support domestic emergencies or federal missions. Available specialties and positions depend on the component and unit.
Commissioning Paths
Qualified civilian RNs with a BSN may apply for direct commission, complete the required officer training and serve in a drilling unit. Active-duty officers may also seek reserve assignments after their obligation, allowing them to continue military service alongside civilian nursing.
Some ROTC nursing graduates commission through Reserve contracts, combining a civilian nursing career with military service and its initial training requirements.
Drill and Training Commitment
The usual part-time schedule combines monthly drills with annual training, but additional training or mobilization can require more time. Nurses must maintain the licensure and clinical competence required for their role; they should check the applicable state-board and Army requirements rather than assume that drilling alone satisfies them.
Reserve Pay
For four drill periods, an O-3 earns about $737.88 per weekend with under two years of service, or $902.72 at the over-three-years pay step. During annual training and mobilization, basic pay follows the active-duty daily rate for the officer’s grade and years of service.
Component Comparison
| Feature | Active Duty | Army Reserve | Army National Guard |
|---|---|---|---|
| Commitment | Full-time | 1 weekend/mo + 2 weeks AT | 1 weekend/mo + 2 weeks AT |
| Monthly Base Pay (O-3) | $5,534+ | ~$738/weekend drill | ~$738/weekend drill |
| Healthcare | Active-duty member coverage; family costs vary | TRICARE Reserve Select ($57.88/mo individual) | TRICARE Reserve Select ($57.88/mo individual) |
| Education Benefits | Full Post-9/11 GI Bill | MGIB-SR ($493/mo) or Post-9/11 if activated | State tuition waivers (varies) + MGIB-SR |
| Deployment Tempo | Moderate to high (unit cycle) | Low to moderate (mobilization-dependent) | Low to moderate (mobilization-dependent) |
| Command Opportunities | Ward leadership, MTF command track | Medical unit OIC billets | State-mission medical unit command |
| Retirement | 20-year pension (BRS) | Points-based, collect at 60 | Points-based, collect at 60 |
Civilian Career Integration
Reserve and Guard nurses can combine civilian clinical work with military service. An ICU nurse, for example, may bring civilian critical-care experience to a military hospital team while gaining field experience that broadens their civilian practice.
USERRA provides employment and reemployment protections for eligible military service, subject to the law’s requirements. Employer Support of the Guard and Reserve can help service members and employers understand those obligations.
Post-Service Opportunities
Nurse Corps experience can strengthen a civilian resume through varied ward assignments, early leadership, field care in austere settings and funded graduate education. Together, those experiences may give separating officers a broader clinical and management background than many civilian peers.
Civilian Career Prospects
| Civilian Role | Median Annual Salary | Job Outlook (2024-2034) |
|---|---|---|
| Registered Nurse | $93,600 | +6% (faster than average) |
| Nurse Practitioner / CRNA / Nurse Midwife | $132,050 | +35% (much faster than average) |
| Medical and Health Services Manager | $117,960 | +23% (much faster than average) |
| Travel Nurse (specialty) | $95,000-$130,000+ | Strong demand |
Data from BLS Registered Nurses and BLS Nurse Anesthetists, Midwives, and Practitioners.
Transition Resources
The Soldier for Life Transition Assistance Program helps officers plan a move to civilian work. Clinical credentials, charge-nurse experience and team leadership can strengthen an application, but employers set their own requirements. Eligible veterans may also qualify for hiring preferences in federal employment.
Hiring Our Heroes and American Corporate Partners offer transition support. VA nursing positions are another option to investigate, with eligibility, credit for experience and pay determined by the specific vacancy.
Credentials and Licensing
Officers preparing to leave service should check the renewal, licensure and certification requirements for their destination and specialty. Military credentials and graduate education can support a civilian transition, but separation does not automatically renew a license, maintain specialty certification or establish eligibility for every civilian position.
The Post-9/11 GI Bill gives up to 36 months of school benefits. Officers who joined with a BSN can use it for a DNP or MSN. Transferring benefits to dependents generally requires at least six years of service, an agreement to serve four more years, Department of War approval and an eligible dependent enrolled in DEERS. The transfer must be requested while serving on active duty or in the Selected Reserve; exceptions follow the applicable policy.
Is This a Good Job for You? The Right (and Wrong) Fit
The Right Fit
The path can suit nursing students who want leadership responsibilities and a career caring for soldiers and their families. Eligible students can explore ROTC alongside nursing school, while qualified nurses can consider direct commissioning. Funding, training and service obligations depend on the selected program rather than on the applicant’s preferences alone.
Army nursing may appeal to civilian nurses seeking more varied ward work, faster loan repayment or experience in austere settings. The range of patients, field missions and leadership opportunities makes it a different career proposition from routine private-sector ward assignments.
Reserve or Guard service may suit nurses who want to keep a civilian practice while developing military field skills and earning retirement points. The commitment includes drills, required training and possible mobilization, so it needs to fit alongside civilian work.
Potential Challenges
Travel or per-diem ICU nursing in high-cost cities may pay more than O-2 or O-3 basic pay. A useful comparison also includes housing allowances, healthcare, paid leave, retirement benefits and the conditions of the actual civilian offer.
Frequent moves every two to three years can be difficult for nurses who value long-term patient relationships or roots in one unit. Army formularies, credentialing requirements and the chain of command also limit clinical autonomy compared with many civilian hospitals.
Some officers expect primarily ward assignments but find that leadership responsibilities grow quickly. By O-3, staff and quality-management duties can reduce time available for direct patient care, a shift that suits some nurses more than others.
Career and Lifestyle Alignment
For a nursing student finishing a BSN with loans and no military background, a four-year ROTC obligation may offer a structured path with loan relief, early leadership and funded AOC education.
A civilian RN considering a Reserve commission needs to weigh military training and possible mobilization against the demands of civilian practice. The two roles can broaden experience, but their schedules and responsibilities require planning.
More Information
Contact an AMEDD nurse recruiter about current accession routes, bonuses and available assignments. Nursing students should also consult their ROTC program’s nursing adviser. Enlisted applicants considering AECP can find current application cycles and requirements at Army recruiting’s AECP page.
- OCS candidates: prepare for GT 110 with our ASVAB for OCS study guide
Explore more Army medical officer careers. Start with the Medical Corps Officer (MC) for Army doctors. Read the Medical Service Corps Officer (MS) for health care bosses and allied health staff.