Army Family Medicine Physician (61H)
A family medicine physician in the Army sees the widest range of patients of any doctor in uniform. One appointment is a soldier with a sprained ankle. The next is a pregnant spouse, then a retiree with diabetes, then a toddler with an ear infection.
The officer is trained for all four and does not hand any of them to someone else without a reason.
The specialty code is 61H, Family Medicine, in the Army Medical Corps. It is the corps’ generalist physician role, and the Army depends on it. Family medicine contributes broad primary care alongside the other professions in the military health system; staffing and supervision arrangements depend on the clinic.
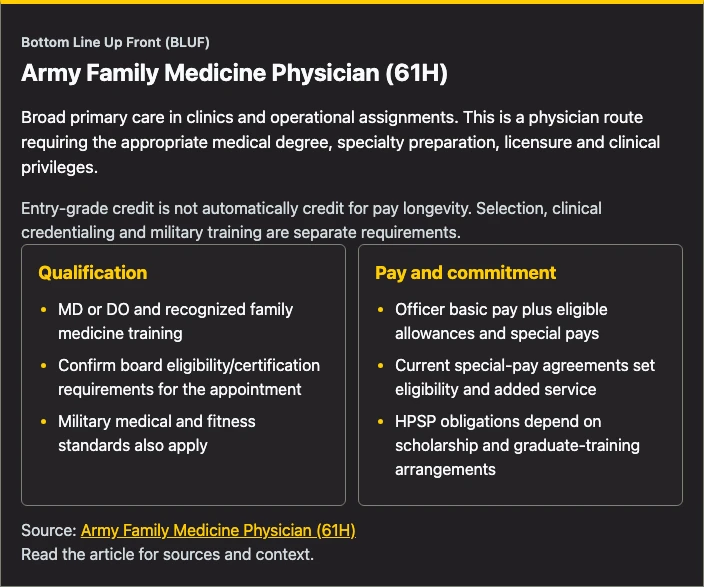
Broad primary care in clinics and operational assignments. This is a physician route requiring the appropriate medical degree, specialty preparation, licensure and clinical privileges.
Entry-grade credit is not automatically credit for pay longevity. Selection, clinical credentialing and military training are separate requirements.
Qualification
- MD or DO and recognized family medicine training
- Confirm board eligibility/certification requirements for the appointment
- Military medical and fitness standards also apply
Pay and commitment
- Officer basic pay plus eligible allowances and special pays
- Current special-pay agreements set eligibility and added service
- HPSP obligations depend on scholarship and graduate-training arrangements
Source: Army Family Medicine Physician (61H)
Read the article for sources and context.
On this page
Job Role and Responsibilities
Army family medicine physicians (61H) provide care at every level of the health service support system. They treat the common problems that fill most of a clinic day, including general medicine, women’s health, pediatrics, psychiatry and orthopedics, in inpatient and outpatient settings. They also support surgical teams through triage, stabilization, surgical assistance and pre- and post-operative care.
The Army’s classification manual describes the specialty in one long sentence: family medicine officers care for 85 percent of patients whose problems fall in general medicine, gynecology, obstetrics, psychiatry, preventive medicine, pediatrics and orthopedics. The rest go to specialists. That sentence explains the job better than a task list does.
The 61H officer sorts the common from the serious and treats most of what walks in.
In a military treatment facility the work looks like primary care anywhere. There are scheduled appointments, same-day sick call, preventive visits, minor procedures, medication reviews and the documentation that follows each one. What changes is the patient mix.
Half the panel may be active duty soldiers whose units need them back at work, and the other half may be spouses, children and retirees with the ordinary problems of a family practice.
Command and Leadership Scope
A junior 61H officer leads a small clinical team made up of medics, nurses and technicians. The officer sets the pace of the clinic day and decides which patients need more than primary care.
Rank brings larger billets. A major or lieutenant colonel may run a primary care clinic as officer in charge, which means owning staffing, access to appointments, quality measures and the credentialing of every provider in the section. At a larger treatment facility the officer may serve as chief of the department of primary care.
There is a second leadership lane that most physicians do not have. Family medicine officers fill battalion surgeon billets, where the officer advises a combat arms commander on the health of the formation. That job is not primarily clinical.
It is a staff role that turns medical data into readiness advice, and it puts a physician in a maneuver unit rather than a hospital.
Specific Roles and Designations
| Designation | Code | What it covers |
|---|---|---|
| Family Medicine Physician | 61H | The primary specialty. Requires completed family medicine residency training |
| Operational Medicine | 60A | Duty AOC used for command and staff positions that mix clinical work with planning and supervision |
| Medical Proficiency Designator | 9A to 9E | Clinical proficiency level and deployability status |
The 60A code is easy to misread. The classification manual states that operational medicine is used only as a duty AOC, which means it labels a position rather than replacing the officer’s clinical specialty. A 61H officer serving as a battalion surgeon still holds 61H.
The 60A code marks the billet.
The 9A to 9E designators matter more than most new physicians expect. They record proficiency and whether the officer is deployable. A physician in the first year of graduate medical education carries 9E and is not a mobilization asset.
The designator moves as training and board status move.
Mission Contribution
A battalion cannot train if its soldiers cannot see a doctor. Family medicine is the layer that keeps small problems from becoming lost training days, and it is the filter that decides which patients reach a specialist. When the primary care network is short of physicians, appointments back up, soldiers wait, and commanders hear about it.
The specialty also carries most of the Army’s preventive work. Immunizations, physical exams, chronic disease follow-up and screening all run through primary care. None of it is dramatic.
All of it decides how many soldiers are medically ready on any given day.
Technology, Equipment, and Systems
Garrison practice uses the military health system’s electronic record, standard diagnostic equipment, point-of-care testing and the scheduling and referral systems that connect a clinic to a hospital. Most 61H officers also perform office procedures, so they work with the instruments for minor surgery, joint injections, splinting and women’s health exams.
Field practice is thinner. A battalion aid station has a limited set of equipment and no imaging. The physician works from examination findings, a small pharmacy and the evacuation system.
Deciding who needs to move is often the most consequential call of the day.
Salary and Benefits
Base Pay (2026)
Physicians commonly enter active clinical service as captains, with appointment grade determined by the approved accession record. Entry-grade credit and years credited for basic pay are separate calculations; a medical degree alone should not be treated as extra years on the pay table.
| Rank | Pay Grade | Years of Service | Monthly Base Pay | Annual Base Pay |
|---|---|---|---|---|
| Captain (CPT) | O-3 | 2 or less | $5,534 | $66,409 |
| Captain (CPT) | O-3 | Over 4 | $7,383 | $88,592 |
| Major (MAJ) | O-4 | 2 or less | $6,295 | $75,535 |
| Major (MAJ) | O-4 | Over 8 | $8,816 | $105,797 |
| Major (MAJ) | O-4 | Over 12 | $9,888 | $118,660 |
Source: DFAS 2026 pay tables. Figures reflect the 2026 pay raise.
The table shows 2026 officer basic pay. Figures are rounded to whole dollars and exclude allowances and special pays; the service-time labels identify the applicable pay brackets.
Special Pays
Physician compensation can include Board Certification Pay, Incentive Pay and a Retention Bonus when the officer meets the applicable conditions. The DFAS Medical Corps table identifies these categories and labels its published rates as maximum amounts, with service-specific amounts determined by the service personnel office.
A listed maximum is not an individual offer. Before accepting an accession or retention agreement, ask the Army medical recruiter or special-pay office to identify the current fiscal-year authority, the qualifying specialty and training status, and the additional service obligation in writing. Compare the full compensation package rather than basic pay alone.
Additional Benefits
Officers receive Basic Allowance for Subsistence of $328.48 per month. Basic Allowance for Housing depends on duty station, grade and dependent status, and it is not taxed. Active duty members receive care without out-of-pocket costs under the applicable TRICARE rules.
Family members enrolled in Prime generally have no costs for covered care obtained through the required referral process; point-of-service rules and the selected plan still matter. Active duty officers earn 30 days of paid leave each year.
For officers covered by the Blended Retirement System, 20 years of active service yields a pension equal to 40 percent of the highest 36-month average of basic pay. BRS includes an automatic 1 percent Thrift Savings Plan contribution after 60 days and up to 4 percent in matching contributions after two years, when the member contributes at least 5 percent. Members who entered before 2018 and did not opt into BRS retain their applicable legacy retirement plan.
Work-Life Balance
Family medicine is one of the more predictable physician schedules in the Army. Clinics keep office hours on weekdays, and after-hours coverage is usually shared across a call group rather than carried alone. That is a real difference from emergency medicine or surgery, where the schedule follows the operating room or the department.
Predictable does not mean fixed. Field training, deployments and temporary duty assignments interrupt the calendar, and a battalion surgeon spends time with the unit rather than in the clinic. The officer who wants a clinic-only career should know that the operational side of the job comes with the uniform.
Qualifications and Eligibility
Commissioning Sources
Four routes lead to the Medical Corps, and all of them end with the same requirements: an MD or DO, completed residency training in family medicine, and a license to practice.
Health Professions Scholarship Program (HPSP). The Army pays tuition, mandatory fees and a monthly stipend at a civilian medical school. The student commissions as an officer during school and completes a 45-day active duty training period each year.
Uniformed Services University of the Health Sciences (USUHS). The federal medical school in Bethesda, Maryland, charges no tuition and pays students as officers throughout the four-year program. Graduates serve a longer obligation.
Direct Commission. A licensed physician who already holds a medical degree can commission directly and complete a condensed officer course. This route is common for Reserve and National Guard physicians.
Financial Assistance Program. The Army pays an annual grant and a monthly stipend to physicians already in a residency or fellowship. It is the route for someone who decided on military service after starting training.
Commissioning Requirements
| Path | Degree | Licensure | Service Obligation |
|---|---|---|---|
| HPSP | MD or DO, in progress or complete | Required before active duty practice | Depends on scholarship length and graduate training; commonly 3–4 years for the scholarship commitment |
| USUHS | MD conferred by USUHS | Required before active duty practice | 7 years after residency |
| Direct Commission | MD or DO, complete | Active state license | Depends on the appointment and any incentive agreement |
The Army’s medical accession guidance describes commitments by program rather than a universal four-year HPSP obligation. Residency, fellowship and incentive agreements can affect the total commitment, so obtain the complete obligation calculation for the chosen route before signing.
All paths require U.S. citizenship, a qualifying physical examination and a security clearance. Age limits and waivers change with recruiting policy and prior service, so an applicant near a limit should ask a recruiter rather than assume the answer.
Test Requirements
Medical Corps officers commission as health professionals, so the ASVAB does not apply. HPSP and USUHS applicants take the MCAT for medical school admission. Licensure later requires passing the national medical exams that each state board accepts, as the Bureau of Labor Statistics notes in its physician and surgeon profile.
Military applicants compete for residency positions through the Joint Graduate Medical Education Selection Board, commonly called the military match. Civilian training requires the appropriate service approval and its own application arrangements.
Branch Selection and Assignment
Physicians do not compete for a branch the way a cadet competes for infantry. They are accessed into the Medical Corps, then designated by specialty after residency training. The specialty code follows the training, not a branching board.
That means the choice of specialty happens at the residency match rather than at commissioning, and it is the decision that shapes the rest of the career.
Upon Commissioning
Physicians typically enter at O-3 with credit for graduate education. The 61H designation applies once family medicine residency training is complete. Before that, the officer holds a training status and the 9E designator that goes with it.
Work Environment
Setting and Schedule
The primary workplace is a primary care clinic at a military treatment facility, on a large installation or a small one. The day is a mix of scheduled visits, walk-ins and administrative work, with the volume set by how many soldiers and family members the clinic serves.
Deployed and field settings look different. A battalion surgeon may work from an aid station with a small team, seeing patients between training events and advising the commander. A physician assigned to a forward medical unit may work in a facility that is closer to a small hospital than a clinic.
Leadership and Chain of Command
A junior 61H officer reports through the clinic chain to the department chief and the facility commander. Clinical authority comes from licensure and granted privileges. Military authority comes from appointment and assignment.
The officer needs both, and the two are not the same.
Officer-NCO Dynamic
The senior NCO in a clinic or medical unit runs enlisted training, discipline and day-to-day readiness. The physician owns the clinical standard and the patient care decisions. A physician who tries to manage the enlisted side directly tends to have a harder tour than one who uses both lanes properly.
Staff vs. Command Roles
Family medicine officers move between clinical billets and staff work. Junior officers spend most of their time in the clinic. Mid-grade officers add staff time on quality, credentialing or readiness committees.
Senior officers spend more time on the staff side, and the ones who take command of a clinic, a department or a medical activity move further still.
Training and Skill Development
Pre-Commissioning Training
HPSP students complete a 45-day annual training period, usually at a military medical facility or with a unit. USUHS builds military training into the curriculum, with physical training, field exercises and leadership coursework running alongside clinical education.
Basic Officer Leader Course (BOLC)
Medical officers attend Army medical officer training at Fort Sam Houston, Texas. The Army AMEDD overview describes different active and Reserve training lengths and notes that specialty and prior military experience affect the requirement.
Use the course reservation and accession instructions for the actual schedule. Applicants should confirm whether they owe a direct-commission course, BOLC, or both, and which portions require resident attendance; a generic three-phase timetable is not a reliable substitute for those orders.
Graduate Medical Education
Family medicine residency takes three years after medical school and is the training that defines the specialty. Residents rotate through inpatient medicine, obstetrics, pediatrics, surgery, behavioral health and outpatient practice, because the specialty covers all of them.
Board certification comes after residency through the American Board of Family Medicine or the American Osteopathic Board of Family Physicians. Some physicians add a fellowship, most commonly sports medicine, which takes another year and opens a different set of assignments.
Professional Military Education
Clinical training and Army professional military education serve different purposes. Residency establishes specialty preparation; military courses develop the officer for operational planning and wider leadership responsibilities.
Physicians should plan required military schooling with their career manager alongside residency, fellowship and clinical assignments. Course eligibility, delivery format and completion deadlines depend on the officer’s record and current Army guidance, so a single years-of-service timetable should not be treated as a promotion guarantee.
Additional Training
Operational assignments open additional schools. Airborne School runs about three weeks. Air Assault School runs about ten days.
Physicians assigned to aviation units complete flight surgeon training, which adds a separate qualification and a flying duty medical requirement. The Army also funds civilian graduate education for selected officers through long-term health education and training.
Career Progression and Advancement
Career Path
| Rank | Grade | Typical Time in Service | Key Assignment |
|---|---|---|---|
| Captain | O-3 | 0 to 9 years, includes residency | Clinic physician, battalion surgeon |
| Major | O-4 | 10 to 15 years | Clinic officer in charge, department staff |
| Lieutenant Colonel | O-5 | 15 to 20 years | Department chief, corps medical staff |
| Colonel | O-6 | 20 to 27 years | Medical treatment facility command, medical command staff |
Appointment grade and later promotion are separate decisions. Officers should confirm their date of rank, military education requirements and promotion eligibility with their career manager rather than infer a promotion date from the clinical training timeline.
Promotion Factors
A competitive file combines clinical credibility with operational experience. Officer evaluation reports carry the most weight, and the strongest ones show a physician who led something beyond a patient panel. Deployments, assignments with maneuver units and staff work all help.
So does finishing professional military education at the right point rather than late.
Clinical service alone limits how far a Medical Corps officer can go. The board selects for officers who can run a medical organization, not only for good clinicians.
Broadening and Functional Areas
Broader work can include teaching, research, clinical-service leadership and medical staff assignments. These roles should be planned around the officer’s clinical qualifications, privileges and the available positions.
Health administration has its own Army classifications and appointment requirements. The officer classification manual lists 70A Health Care Administration and 70B Health Services Administration; it does not establish an automatic “FA70” progression for a physician after company-grade service.
Physical Demands and Medical Evaluations
The officer classification manual lists correctable vision, manual dexterity, normal color perception, a physical profile of 222222 and a Moderate (Gold) physical-demands category for this specialty. The Army’s published Gold OPAT explanation gives these thresholds:
- Standing long jump: 120 cm.
- Seated power throw: 350 cm.
- Strength deadlift: 120 lb.
- Interval run: 36 shuttles.
The deadlift is 120 pounds, approximately 54 kg. Applicants should confirm which accession assessments apply to their medical appointment; the occupational classification and the recurring Army Fitness Test are separate requirements.
Officers also take the Army Fitness Test (AFT), which replaced the ACFT on June 1, 2025. For ages 17 through 21, the official AFT scoring standards list:
| Test event | Male 17-21 minimum | Female 17-21 minimum |
|---|---|---|
| Three-repetition maximum deadlift | 150 lb | 120 lb |
| Hand-release push-ups | 15 | 11 |
| Sprint-drag-carry | 2:28 or faster | 3:15 or faster |
| Plank | 1:30 or longer | 1:30 or longer |
| Two-mile run | 19:57 or faster | 22:55 or faster |
Older age groups have different standards. Family medicine is not a designated combat specialty, so the general standard of 300 points overall with at least 60 per event applies.
The specialty itself carries no flight physical requirement. A physician who takes a flight surgeon assignment adds that qualification and its medical evaluation, which is an assignment requirement rather than part of 61H.
Deployment and Duty Stations
Deployment Details
Family medicine officers deploy with the units they support. A battalion surgeon moves with the battalion. A physician assigned to a medical company or a combat support hospital deploys with that unit on its rotation.
The tempo depends on the unit and the period rather than on the specialty.
Deployed practice shifts toward acute problems and away from chronic disease management. The physician sees injuries, infections and the ordinary illnesses of a young population, with limited imaging and a pharmacy that carries what it carries. Evacuation decisions carry more weight because the next level of care is farther away.
Duty Station Options
Family medicine officers serve at military treatment facilities of every size, from large medical centers to small clinics on remote installations. Assignment is managed by Human Resources Command, and officers submit preference sheets that are weighed against the needs of the Army.
Small installations are worth considering on purpose. A clinic with two physicians gives a junior officer more independence than a large department does, and the officer learns administration earlier because there is no one else to do it.
Risk, Safety, and Legal Considerations
Job Hazards
The clinical hazards are ordinary primary care hazards: exposure to infectious disease, needlestick injury and the strain of a full appointment schedule. Deployed practice adds the hazards of the location itself, including indirect fire, movement risk and the stress of working in a small team far from a hospital.
Safety Protocols
Clinics run on standard precautions, sharps handling rules and infection control policy. Deployed aid stations add force protection requirements and casualty decontamination procedures. The physician is responsible for enforcing these inside the section, not only for following them.
Legal and Command Responsibility
A family medicine physician holds clinical authority through licensure and granted privileges, and military authority through appointment. Both carry accountability. A clinic officer in charge answers for the clinical standards of the section, including adverse events, credentialing and quality review.
Relief for cause is a real possibility for officers who hold command. It ends a career path regardless of clinical skill, and the standard is whether the officer led the organization properly, not only whether the officer practiced well.
Impact on Family and Personal Life
Family Considerations
Family medicine is easier on family life than most physician specialties in the Army, because clinic hours are predictable and call is shared. The disruptions come from the military side: permanent change of station orders, field training and deployments.
Each move means a new facility, a new team and a new round of credentialing. Spouses in licensed professions face their own licensing transfer with every move. Family support centers, family readiness groups and spouse employment programs are available at most installations and are worth using.
Dual-Military and Family Planning
Dual-military couples face the problem of coordinating two assignment cycles. The Army manages this through the married army couples program when both members are eligible, and it works best when both service members raise the issue early rather than at orders time.
Reserve and National Guard
Component Availability
The Army Reserve and the Army National Guard both carry family medicine physicians. Direct commission is a common entry route for a practicing civilian physician who wants to serve part time, and Reserve and Guard physicians attend a condensed BOLC rather than the full active duty course.
Drill and Training Commitment
A common training schedule is one weekend per month and two weeks of annual training; schools, readiness duties and mobilization can add time. A drill weekend counts as four drill periods, and each period pays one-thirtieth of monthly basic pay. An O-3 with less than two years of service earns $737.88 for a standard drill weekend.
Part-Time Benefits
TRICARE Reserve Select premiums for 2026 are $57.88 per month for the member alone and $286.66 for member and family. The Montgomery GI Bill Selected Reserve pays $493 per month for up to 36 months of education benefits. Retirement is points-based rather than a 20-year pension, and the points come from drills, annual training and mobilization.
Comparison
| Factor | Active Duty | Army Reserve | Army National Guard |
|---|---|---|---|
| Commitment | Full time | One weekend per month, two weeks per year | One weekend per month, two weeks per year |
| Pay basis (O-3, under 2 years) | $5,534 basic pay | $737.88 per drill weekend | $737.88 per drill weekend |
| Healthcare | TRICARE Prime, no premiums | TRICARE Reserve Select, premiums apply | TRICARE Reserve Select, premiums apply |
| Education | Tuition assistance, Post-9/11 GI Bill | MGIB-SR, Post-9/11 after qualifying active duty | MGIB-SR, state tuition waivers in many states |
| Deployment tempo | Follows the unit | Unit rotations and individual mobilization | State missions and federal mobilization |
| Command opportunity | Clinic, department, facility | Medical company and detachment command | Medical company and detachment command |
| Retirement | 20-year pension plus TSP | Points-based at age 60 | Points-based at age 60 |
Civilian Career Integration
The part-time model suits a physician who already has a civilian practice and wants military service without leaving it. Federal law protects the civilian job during mobilization under the Uniformed Services Employment and Reemployment Rights Act, and many employers treat reserve service as a plus rather than a burden.
Post-Service Opportunities
Transition to Civilian Life
Family medicine transfers to civilian practice with almost no friction. The residency training is the same, the board certification is the same and the license is the same. A departing physician must document completed training, current licensure, board status and the credentials required by the civilian employer.
The operational experience is the part civilian employers notice. Physicians who served as a battalion surgeon, ran a clinic or deployed with a unit bring management experience that most civilian family physicians do not have until much later in their careers.
Civilian Pay and Outlook
| Occupation | Median Annual Wage (May 2025) | Job Outlook, 2025 to 2035 |
|---|---|---|
| Family medicine physicians | $244,180 | 3 percent |
| Physicians and surgeons, all | $275,930 | 4 percent |
Source: BLS Occupational Outlook Handbook. BLS reports 114,300 family medicine physician jobs in 2025 and about 22,100 openings per year across all physician and surgeon occupations, mostly from retirement and career change.
Graduate Education and Credentials
The medical degree, the residency certificate and the board certification all carry into civilian life unchanged. The GI Bill can fund additional graduate education, and the Army’s long-term health education and training program can fund a fellowship while the officer is still serving.
Is This a Good Job for You? The Right (and Wrong) Fit
Ideal Candidate Profile
The physicians who do well in family medicine like variety and like people. They are comfortable with the idea that most of what they see will be ordinary and that the skill lies in recognizing the small number of cases that are not. They also tolerate ambiguity, because primary care begins before a diagnosis exists.
The military version adds a requirement that surprises some applicants. The officer has to be willing to leave the clinic. Battalion surgeon time, field exercises and deployments are part of the job, and a physician who wants a purely clinical career will find those assignments frustrating.
Potential Challenges
The appointment schedule is relentless. A full panel means a full day, and the paperwork does not disappear when the last patient leaves. Physicians who expected academic medicine’s pace often find the volume harder than the medicine.
The second challenge is career timing. Residency, then an obligation, then a decision about whether to stay. Physicians who want a long military career need to build an operational record early.
Physicians who intend to leave after the obligation should know that promotion timing and obligation timing do not always line up.
Career and Lifestyle Alignment
For a physician who wants broad clinical work, a predictable schedule and early leadership responsibility, family medicine fits. For a physician who wants to subspecialize, operate or work in a high-acuity environment, another specialty fits better, and the Army has more than 40 of them.
Compare a real civilian offer with the complete Army package, including eligible special pays, allowances, retirement benefits and any service obligation. National wage statistics describe a labor market; they do not establish what an individual physician will earn or guarantee that one route pays more. Location, shifts, clinical scope and control over assignments matter alongside compensation.
More Information
Family medicine is one of more than 40 physician specialties in the Army Medical Corps. Compare it with emergency medicine, which shares the generalist outlook but runs on shift work, or with the physician assistant route, which delivers similar primary care with a shorter training path and a different scope of practice.
A family nurse practitioner is the other comparison worth making. The family nurse practitioner route starts from nursing, takes a master’s or doctoral degree rather than a medical degree, and practices under a different license. The clinical work overlaps.
The training, the pay scale and the legal scope do not.
The most useful next step is a conversation with an Army medical recruiter, who can give current specialty pay figures, current accession bonus amounts and the family medicine residency programs taking applications this cycle.