Army Medical Specialist Corps Officer (SP)
The Army Medical Specialist Corps allows licensed healthcare professionals to continue treating patients while leading soldiers and earning military pay.
The SP Corps is the smallest of the six Army Medical Department (AMEDD) corps. Its four fields are occupational therapy, physical therapy, dietetics and physician assistant practice. This guide explains the route for applicants completing a DPT, OTD, RD or PA credential.
OCS candidates need a GT score of 110 on the ASVAB. Our ASVAB for OCS guide shows you how to reach it.
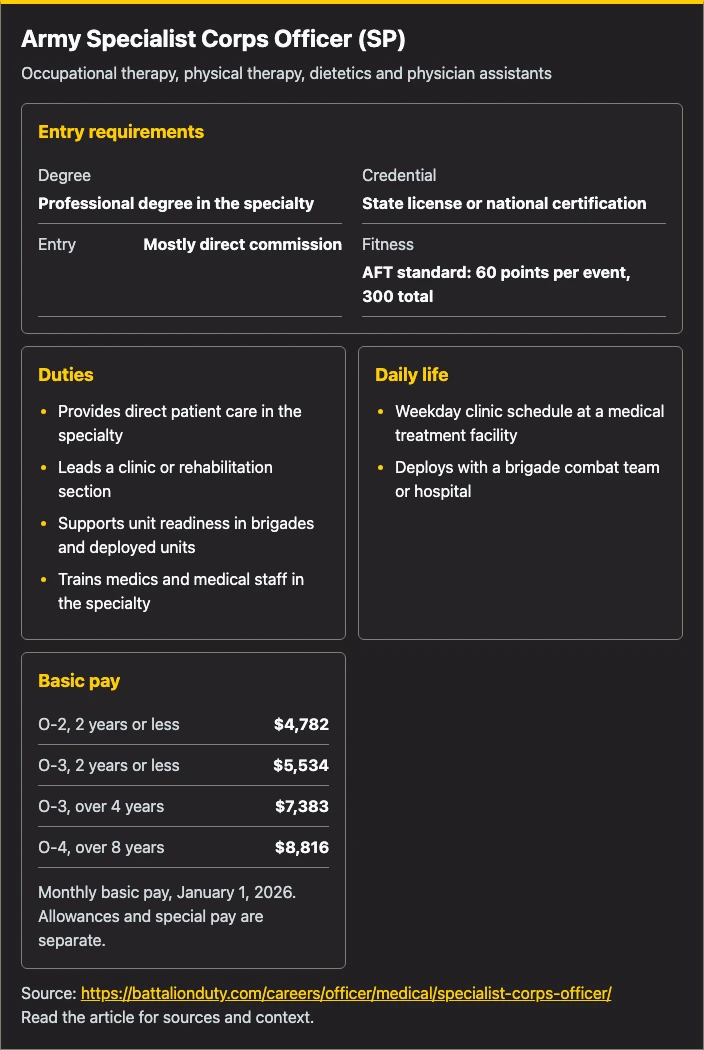
Entry requirements
- Degree
- Professional degree in the specialty
- Credential
- State license or national certification
- Entry
- Mostly direct commission
- Fitness
- AFT standard: 60 points per event, 300 total
Duties
- Provides direct patient care in the specialty
- Leads a clinic or rehabilitation section
- Supports unit readiness in brigades and deployed units
- Trains medics and medical staff in the specialty
Daily life
- Weekday clinic schedule at a medical treatment facility
- Deploys with a brigade combat team or hospital
Basic pay
- O-2, 2 years or less
- $4,782
- O-3, 2 years or less
- $5,534
- O-3, over 4 years
- $7,383
- O-4, over 8 years
- $8,816
Monthly basic pay, January 1, 2026. Allowances and special pay are separate.
Source: https://battalionduty.com/careers/officer/medical/specialist-corps-officer/
Read the article for sources and context.
On this page
Job Role and Responsibilities
Medical Specialist Corps officers provide direct patient care, lead clinics and support unit readiness in Army hospitals, brigade combat teams and deployed units. The four sections are Occupational Therapy (65A), Physical Therapy (65B), Dietetics (65C) and Physician Assistant (65D). Officers maintain the required professional credentials and practice within their specialty’s scope and supervision rules. The corps belongs to the Army Medical Department alongside the Medical Corps, Medical Service Corps and Nurse Corps.
Command and Leadership Scope
Medical Specialist Corps officers do not command combat units. Junior officers (O-1 through O-3) instead lead clinics and enlisted medical technicians while managing patient care and administrative duties.
An O-3 physical therapist at a brigade support battalion may be the only PT supporting thousands of soldiers, requiring independent clinical decisions each day.
At O-4 and above, officers may become unit chiefs supervising multiple clinic staff and directing clinical operations across an Army hospital. They also fill staff positions at major commands, including MEDCOM headquarters, and at schools such as the AMEDD Center and School.
Enlisted specialists support these officers by field: 68L Occupational Therapy Specialists work under 65A, 68F Physical Therapy Specialists under 65B, and nutrition care specialists under 65C. A senior 65A or 65B Major may direct a section of 5 to 15 people.
AOCs, Skill Identifiers, and Designations
| AOC | Title | Discipline |
|---|---|---|
| 65A | Occupational Therapist | Occupational Therapy |
| 65B | Physical Therapist | Physical Therapy (civilian DPT entry) |
| 65C | Registered Dietitian | Dietetics and Clinical Nutrition |
| 65D | Physician Assistant | Physician Assistant (separate accession and bonus track) |
65D (Physician Assistant) is one of the four SP sections. It has its own hiring path and its own bonus plan. This page covers the corps as a whole.
For clinical duties and section-specific requirements, read the occupational therapist, physical therapist, dietitian and physician assistant profiles. This page covers the corps as a whole.
Mission Contribution
Combat readiness depends on soldiers being able to lift, carry and move, as well as maintaining those abilities over time. The SP Corps supports both needs.
Occupational therapists treat arm and hand injuries and provide brain injury rehabilitation. Physical therapists screen incoming soldiers, treat muscle and joint injuries, and help avoid unnecessary surgery. Dietitians develop nutrition plans for performance and eating disorders while also providing clinical nutrition care to hospitalized patients.
Technology, Equipment, and Systems
SP officers work within the Military Health System and use MHS GENESIS, the Defense Department’s electronic health record system.
Physical therapists use tools such as isokinetic dynamometers, goniometers and movement screening kits. Occupational therapists administer cognitive and sensory assessments, create custom orthotics and use adaptive equipment in warrior transition care. Dietitians rely on nutrition software and audit food quality at MEDCOM facilities.

Salary and Benefits
Officer Base Pay (2026)
All figures are 2026 DFAS rates. They took effect on January 1, 2026.
| Rank | Title | Years of Service | Monthly Base Pay |
|---|---|---|---|
| O-1 | Second Lieutenant (2LT) | Less than 2 | $4,150 |
| O-2 | First Lieutenant (1LT) | 2-3 years | $5,446 |
| O-3 | Captain (CPT) | 4-6 years | $7,383 |
| O-3 | Captain (CPT) | 8+ years | $8,126 |
| O-4 | Major (MAJ) | 10 years | $9,420 |
| O-5 | Lieutenant Colonel (LTC) | 16 years | $11,391 |
Most officers enter through direct commission at O-1 and reach O-3 (Captain) within four years. A captain with four to six years of service earns $7,383 per month in base pay.
Special Pays and Bonuses
Officers may qualify for medical incentive or board-certification pay under current eligibility rules. Authorized amounts and obligations depend on the profession and program; confirm the terms that apply to your AOC.
Accession incentives vary by profession and program year. A general advertised healthcare bonus should not be treated as an offer for every OT or PT.
Bonus amounts change each fiscal year according to shortage designations. Confirm the current figure with an AMEDD recruiter rather than treating older amounts as fixed.
Additional Benefits
Officers get the same benefits as any other officer:
- TRICARE: active-duty member coverage and eligible family plans; family costs depend on the plan and care received.
- BAH: a monthly housing allowance based on duty location, rank and dependent status.
- BAS: $328.48 a month for officer food. That is the 2026 rate.
- Pension: the Blended Retirement System (BRS) pays 40% of high-36 pay at 20 years. It also matches TSP contributions up to 5% of base pay from year three.
- Federal Tuition Assistance: up to $4,500 a year for off-duty study. There is a $250 per credit-hour cap.
Work-Life Balance
In garrison, most SP officers work in clinics Monday through Friday, with late calls uncommon outside inpatient settings. Deployment can bring twelve-hour days as often as seven days a week for PTs and OTs, while field exercises may add two to four weeks annually on top of routine clinic duties.
Officers earn 30 days of paid leave per year, accruing 2.5 days each month, and may carry over 60 days.
Qualifications and Eligibility
Commissioning Sources
Most officers enter through direct commission, applying with their professional credentials without first completing ROTC or OCS.
| Commissioning Path | Degree Requirement | GPA | Age Limit | Branch Prerequisite |
|---|---|---|---|---|
| Direct Commission (active duty) | Professional degree in specialty | Varies by board | 42 (waiverable) | State license/national certification |
| ROTC + AMEDD track | Enrolled in professional program | 2.5+ GPA | 31 at commissioning (waiverable) | Sponsoring ROTC program |
| Army-sponsored professional training | Program-specific prerequisites | Program-specific | Program-specific | Meet the selected clinical program’s admissions rules |
AECP is a nursing-degree route into the Army Nurse Corps, not the Specialist Corps. The Medical Specialist Corps identifies its own occupational therapy, physical therapy, nutrition and PA training pathways.
Education Requirements by AOC
- 65A (Occupational Therapist): a master’s degree (MOT) at minimum. The Army runs its own OTD program at Fort Sam Houston. A doctoral degree (OTD) is becoming the norm. State OT license required.
- 65B (Physical Therapist): a Doctor of Physical Therapy (DPT) is required. The program must hold Commission on Accreditation of Physical Therapy Education (CAPTE) approval. State PT license required before commissioning.
- 65C (Registered Dietitian): a bachelor’s degree at minimum. A master’s is preferred. The Commission on Dietetic Registration (CDR) RD credential is required. Supervised practice must be completed.
- 65D (Physician Assistant): see the physician assistant profile for the two accession paths and their education requirements.
Test Requirements
The SP Corps does not require the aviation SIFT. Applicants following a general OCS route should check that program’s published test requirements; direct-commission applicants are assessed on professional qualifications and board requirements. An enlisted entrance score does not replace the clinical credentials for an SP role.
Civilian clinicians who apply by direct commission rarely take the ASVAB. Check the rule for your own case with a recruiter.
Upon Commissioning
Direct commission officers normally enter at O-1 (second lieutenant), but prior service, education and clinical experience may qualify them for credit. Applicants with doctorates may enter at O-2 or O-3, depending on the board’s decision.
Service obligations depend on the accession route, training and incentives accepted. A direct-commission offer and an Army-sponsored professional program may carry different terms; read the written agreement before committing. The Army-Baylor DPT program has its own training and service requirements.
OCS candidates can find a GT study plan in our ASVAB for OCS guide.

Work Environment
Setting and Schedule
SP officers work in military treatment facilities (MTFs), brigade medical companies, warrior transition units and deployed units. Much of the clinical work takes place in exam rooms, rehabilitation gyms or dietetics offices.
A garrison week for a 65B can resemble a busy orthopedic clinic. Unit physical training may precede sick call and appointments, while afternoons include documentation, readiness work and further study. The actual schedule depends on the assignment.
Deployed settings vary, but SP officers serving with a Combat Support Hospital or Brigade Support Medical Company may face limited equipment, long patient backlogs and a broader scope of work than many civilian clinicians encounter.
Staff vs. Command Roles
For an OT or PT, clinical leadership can provide a different kind of responsibility from platoon command. At O-3, that may mean serving as a section officer in charge (OIC) or chief of PT at an MTF, combining patient care with budgets, staffing and readiness work.
At O-4 and above, officers may seek unit chief positions, MEDCOM staff assignments or broadening opportunities such as ROTC instruction, AMEDD school faculty positions and joint staff duty.
Officer-NCO Dynamics
Senior healthcare NCOs and medical technicians bring experience in supply, enlisted discipline and training. The SP officer remains responsible for clinical authority and officer leadership, working with that expertise rather than assuming that either role replaces the other.
Retention and Job Satisfaction
The small SP Corps uses substantial financial incentives to retain officers in shortage AOCs, including 65A in recent years. Officers who stay through O-4 and beyond may value the work itself, pay that exceeds early civilian earnings, and bonuses that help offset education debt.
Officers who leave often cite frequent PCS moves, less clinical autonomy than private practice and leadership duties that reduce time with patients.
Training and Skill Development
Pre-Commissioning
Direct-commission applicants complete the required professional education and credentials before Army training. They generally attend the Direct Commission Course (DCC) rather than enter through ROTC or OCS.
BOLC Pipeline
Direct Commission Course (DCC), Fort Sill, Oklahoma
The AMEDD DCC at Fort Sill introduces civilians to Army officer duties through land navigation, weapons qualification with the M17 pistol and M4 rifle, customs and courtesies, fitness standards and basic leadership. It is a short officer introduction rather than a combat training path.
AMEDD Basic Officer Leadership Course (BOLC), Fort Sam Houston, TX, 10 to 14 weeks
At the Army Medical Center of Excellence, BOLC runs four times a year and covers the Military Health System, AMEDD structure, Army care doctrine and planning. Specialist Corps officers attend alongside MC, MS, AN and DC officers. Course length varies somewhat by AOC and prior service.
AOC-Specific Orientation and Training
After BOLC, officers report to their first base and complete any field orientation required by their MTF or command. Further study can include the Army’s Doctor of Occupational Therapy (OTD) program, delivered by the AMEDD Graduate School. Officers can earn that doctorate while on full-time duty.
| Phase | Location | Length | Focus |
|---|---|---|---|
| Direct Commission Course (DCC) | Fort Sill, Oklahoma | Per current course orders | Military fundamentals, weapons, leadership |
| AMEDD BOLC | Fort Sam Houston, TX | 10-14 weeks | Army medicine, MHS, doctrine, medical planning |
| First-duty orientation | Assigned MTF | Varies | AOC-specific clinical and administrative onboarding |
Professional Military Education (PME)
- Captain’s Career Course (CCC): you attend the AMEDD CCC. It covers company leadership, ops, and Army medicine at the mid level. Most attend as O-3.
- Intermediate Level Education (ILE) / CGSC: selection is tight at O-4. You need it to make O-5.
- Senior Service College: for O-6 and general officer selections. It is very hard to get.
Additional Schools and Education
Officers may attend the three-week Airborne School at Fort Benning, Georgia, or the ten-day Air Assault School at Fort Campbell, Kentucky. Neither is required, but both can broaden assignment opportunities and demonstrate versatility.
Some officers receive Army funding for graduate education, subject to program eligibility and selection. Officers who already hold a DPT or OTD may pursue a subspecialty fellowship or further study in fields such as health administration; funding and service obligations depend on the specific offer.
Before OCS, you need a GT score that passes. See our ASVAB for OCS guide.
Career Progression and Advancement
Career Timeline
| Rank | Typical Time in Grade | Key Assignment |
|---|---|---|
| O-1 (2LT) | 18 months | DCC, BOLC, initial duty station |
| O-2 (1LT) | 18 months | Junior clinician, section OIC |
| O-3 (CPT) | 4-5 years | Chief of section, clinical OIC (KD period) |
| O-4 (MAJ) | 4-5 years | Department chief, MEDCOM staff |
| O-5 (LTC) | 4-5 years | MTF division chief, AMEDD school faculty |
| O-6 (COL) | 3-4 years | MTF commander, MEDCOM G3/G4, corps-level staff |
Promotion from O-1 through O-3 generally follows time in grade and satisfactory performance, but selection for O-4 is more competitive. Boards review Officer Evaluation Reports (OERs), schooling, timely professional military education (PME) and the breadth of assignments. SP officers compete within their branch group rather than against the wider Army.
Key Developmental Positions
A key career milestone is the O-3 section chief, or section officer-in-charge (OIC), assignment, which functions as the SP equivalent of command. Its OER carries substantial weight because it demonstrates both sound clinical care and unit leadership in an O-4 promotion packet.
Functional Areas and Broadening
Officers interested in a different career field should confirm current transfer eligibility and qualifications. Medical Functional Area 70 covers health services specialties in the Medical Service Corps; it is not an automatic progression route for every SP officer. Other broadening or functional-area opportunities have their own selection rules.
Broadening assignments can include ROTC instruction, AMEDD school faculty positions and joint staff duty. Available fellowships and overseas opportunities depend on current programs and selection requirements.
Building a Competitive Record
A strong SP record includes OERs with clear “above center of mass” language, a completed or in-progress doctorate, timely PME, at least one broadening assignment and field experience through a deployment or major exercise in a planning role. Officers who remain entirely in clinic assignments may struggle to advance beyond O-4.
Physical Demands and Medical Evaluations
Army Fitness Test Standards
All Army officers take the Army Fitness Test (AFT), which became standard on June 1, 2025. The test has five events scored from 0 to 100 points each, for a maximum of 500. SP officers follow the general standard, with scoring adjusted for age and sex.
| Event | Abbreviation | General Minimum (per event) |
|---|---|---|
| 3 Repetition Maximum Deadlift | MDL | 60 points |
| Hand Release Push-Up | HRP | 60 points |
| Sprint-Drag-Carry | SDC | 60 points |
| Plank | PLK | 60 points |
| Two-Mile Run | 2MR | 60 points |
Minimum passing total: 300 points (60 per event). Tables are normed by sex and age. The AFT is enforced for full-time officers as of January 1, 2026.
Branch-Specific Physical Requirements
The SP Corps adds no Ranger School, water survival or flight physical requirement beyond the AFT, although officers attending Airborne or Air Assault School must meet those programs’ entry standards.
Medical Standards
Direct-commission applicants must meet Army officer health standards under AR 40-501. Previous injuries, hearing loss or vision concerns may require medical review or a waiver determination. Weapons qualification requirements depend on the assignment and applicable training standards.
Deployment and Duty Stations
Deployment Tempo
SP officers can deploy with medical and operational units. Common assignments include:
- Combat Support Hospital (CSH) or Role 3 medical facility duty in support of theater operations
- Brigade Support Medical Company (BSMC) slot, where a PT or OT goes out with a brigade combat team
- Aid and disaster response missions, where National Guard officers serve often
Deployments run 9 to 12 months for OCONUS tours. Dwell rules usually promise an equal or longer stretch at home in between. They deploy less than MC officers or 68W enlisted medics. This is not a deployment-free career, though.
Primary Duty Stations
You serve where the major Army hospitals are. The main sites:
- Fort Sam Houston, TX (Brooke Army Medical Center, AMEDD Center and School)
- Fort Bragg (Liberty), NC (Womack Army Medical Center)
- Joint Base Lewis-McChord, WA (Madigan Army Medical Center)
- Fort Campbell, KY (Blanchfield Army Community Hospital)
- Landstuhl Regional Medical Center, Germany (OCONUS, very hard to get)
- Tripler Army Medical Center, HI
Officers submit preference lists at HRC. You get a say, not the final call. First-base assignments for direct commission officers are often set during commissioning.
Risk, Safety, and Legal Considerations
Job Hazards
SP officers face ordinary clinical risks, including sharps injuries, patient handling injuries, infections and the strain of treating trauma. Deployments add potential indirect fire, vehicle movement hazards and austere conditions.
For covered claims arising from health care within assigned duties, 10 U.S.C. § 1089 generally makes the federal remedy exclusive of a personal civil action against the clinician. This is not a blanket guarantee that the government pays every claim. Licensing review, adverse evaluations and military discipline remain separate matters.
Legal and Command Responsibility
SP officers are accountable for their conduct and assigned responsibilities under military law. Clinical leadership does not by itself grant authority to impose nonjudicial punishment: Article 15 assigns that authority to commanding officers under its conditions. Clinical errors, improper drug handling, false records and other misconduct can also have consequences.
A relief-for-cause evaluation can have serious career consequences. Promotion boards consider the officer’s record under the applicable selection rules; a single generic statement cannot determine every officer’s promotion outcome.
Safety Protocols
Risk management applies to clinic work, including infection control, safe patient handling and movement plans. In deployed settings, Tactical Combat Casualty Care (TCCC) guidance informs trauma care, including the work of officers whose primary role is not trauma medicine.
Impact on Family and Personal Life
PCS Tempo
PCS moves commonly come every two to three years, with timing largely set by the Army. For spouses in licensed professions, each move may bring new licensing requirements. Army spouse employment programs and base offices can help, but cross-state licensing remains a practical concern.
Support Systems
- Army Community Service (ACS): financial counseling, employment help, and family ready plans at each base
- Family Readiness Group (FRG): a unit-level family aid net, busiest during deploys
- TRICARE: eligible family coverage, with costs determined by the selected plan and care received
Family healthcare costs depend on the beneficiary’s plan and care received. Use the current TRICARE costs and fees to compare premiums, deductibles, copayments and other expenses rather than assume all family care is free.
Dual-Military Considerations
Dual-military Army couples can seek joint-domicile consideration through the Married Army Couples Program. Compatible clinical specialties may offer suitable positions at the same installation, but both members need available assignments and approval. Plan for the possibility of separate moves or duty stations.
Reserve and National Guard
Component Availability
SP Corps serves in both the Army Reserve and the Army National Guard. Reserve officers work at Army hospitals tied to Reserve units. Many also hold civilian clinic jobs while drilling one weekend a month.
Reserve service can suit clinicians who want to maintain a civilian job or private practice while using their skills in an Army setting. Additional training or mobilization can require time beyond the usual part-time schedule.
Commissioning Paths
Reserve applicants should follow the current AMEDD accession and training instructions for their AOC and prior service. HRC’s Reserve AMEDD guidance distinguishes course requirements; a universal two-week BOLC claim is not a reliable plan. The responsible accession staff and issued orders control the actual sequence and dates.
After completing an active-duty service obligation, officers may seek reserve positions. They should confirm available billets, transfer eligibility and retention of rank and specialty rather than assume that a transfer is automatic. The Individual Ready Reserve and Selected Reserve have different participation requirements.
Drill Commitment and Pay
Standard Reserve service involves one weekend per month, equivalent to four drill periods, plus two weeks of annual training. An O-3 with fewer than two years of service earns $737.88 per drill weekend for four drills, while an O-3 with three years earns $902.72.
Reserve officers may serve additional clinic readiness days, particularly when preparing with a medical unit for deployment.
Healthcare and Education Benefits
- TRICARE Reserve Select: $57.88 a month for member-only coverage. Member plus family costs $286.66 (2026 rates). That is far below most civilian employer plans.
- Federal Tuition Assistance: the same $4,500 yearly cap as full-time duty. Drilling Reserve and Guard members can use it.
- Montgomery GI Bill - Selected Reserve (MGIB-SR): $493 a month for up to 36 months. You can use it while drilling, with no call-up required.
- State tuition waivers: many states give free or reduced in-state tuition to Army National Guard officers. Benefits differ by state.
Retirement
Reserve retirement is points-based rather than a time-in-grade pension. A drill weekend earns four points, and annual training earns one point per day. Twenty “good years” with at least 50 points each qualify an officer for retirement pay, normally beginning at age 60. Qualifying deployment on federal orders can lower that age by 90 days for each 90 consecutive days of full-time duty, down to a minimum of age 50.
Active Duty vs. Reserve vs. Guard Comparison
| Factor | Active Duty | Army Reserve | Army National Guard |
|---|---|---|---|
| Commitment | Full-time | 1 weekend/month + 2 weeks AT | 1 weekend/month + 2 weeks AT |
| Monthly pay (O-3, 4-6 yrs) | $7,383 base pay | ~$902 per drill weekend | ~$902 per drill weekend |
| Healthcare | TRICARE Prime ($0 premium) | TRICARE Reserve Select ($57.88-$286.66/mo) | TRICARE Reserve Select ($57.88-$286.66/mo) |
| Education | Full TA + Post-9/11 GI Bill | TA + MGIB-SR | TA + MGIB-SR + state tuition waivers |
| Deployment tempo | Moderate (1 per 2-4 years) | Lower; mobilization-dependent | Lower; state/federal missions |
| Command opportunities | Clinical chief, dept. chief, MTF leadership | Reserve medical unit leadership | State medical unit leadership |
| Retirement | 40% of high-36 at 20 years | Points-based, collect at 60 | Points-based, collect at 60 |
Civilian Career Integration
Reserve and Guard service can fit alongside a civilian career: a physical therapist may drill one weekend a month while earning additional income, treating Army cases and accumulating retirement points without abandoning private practice. USERRA prohibits employers of any size from penalizing employees for qualifying drill or deployment service, with enforcement handled by the Department of Labor’s VETS office.
Staff in ortho, sports medicine, and rehab find Reserve duty fits their caseload well.
Post-Service Opportunities
Civilian Transition
SP officers can leave the Army with current professional credentials and clinical experience, unlike combat arms officers who may need occupational retraining. An officer leaving after eight years may retain an active DPT license, board certification and clinical hours, alongside management experience many civilian clinicians acquire later.
Army transition programs include the Soldier for Life Transition Assistance Program (SFL-TAP). It offers resume workshops, hiring events, and LinkedIn training. Hiring Our Heroes and the American Corporate Partners (ACP) mentor program aim at officers. Both help them move into health care management.
Veterans Affairs (VA) hospitals employ former Army clinicians in patient-care and leadership roles. Veterans’ preference may apply to eligible applicants under the rules for the particular federal position.
Civilian Career Prospects
| Civilian Role | Median Annual Salary (BLS, May 2024) | Job Outlook (2024-2034) |
|---|---|---|
| Physical Therapist | $101,020 | +11% (much faster than average) |
| Occupational Therapist | $98,240 | Faster than average |
| Registered Dietitian/Nutritionist | $74,770 | Faster than average |
| Healthcare Administrator/Manager | $134,560 | +28% (much faster than average) |
Source: U.S. Bureau of Labor Statistics Occupational Outlook Handbook.
The healthcare administration figure may be relevant to former SP officers applying for clinic management, hospital operations or network leadership roles. Civilian eligibility depends on the position’s qualifications, rather than an assumed military functional-area pathway.
Graduate Education and Credentials
The Post-9/11 GI Bill provides tuition and housing benefits for eligible study after service, including qualifying graduate education. Benefit levels, school type, enrollment and current annual caps affect the amount paid. Check current VA rates before budgeting for an MBA or fellowship.
Army clinic time counts toward state license transfer in most states. Many national cert bodies accept Army service records toward more study. That includes APTA, AOTA, and CDR. Check with your own board, since rules differ.
Is This a Good Job for You? The Right (and Wrong) Fit
The Right Fit
This branch may suit clinicians who want patient care and leadership responsibilities early in their careers. An OT or PT leading a section is responsible for enlisted technicians as well as clinical work. That combination can be appealing, provided regular moves and the other demands of military service fit your plans.
Compare a written Army offer with the actual civilian opportunities available to you, including grade and service credit, applicable allowances, healthcare, retirement and the added obligations attached to incentives. Bonus eligibility and amounts vary by profession and program year; do not use a general advertised range as a guaranteed SP accession offer.
The corps may particularly appeal to clinicians who enjoy teaching, want overseas assignments or hope to research complex military cases, such as blast-related brain injuries, amputee rehabilitation and combat athlete care.
The Wrong Fit
The Army is less suitable for clinicians who want to maintain the same patient panel in one city for twenty years. PCS moves disrupt continuity, may require licenses in more than one state and can bring additional paperwork. Clinical autonomy has limits as well: a senior Medical Corps physician or unit chief may overrule a treatment plan, something described here as less common in private practice.
Some clinicians find military structure, fitness requirements or deployment readiness difficult. A three-year commitment can feel lengthy if an assignment proves to be a poor fit.
Guard or Reserve as a Middle Path
For clinicians seeking military credentials, bonuses and retirement benefits without regular PCS moves, the Army Reserve or National Guard may offer a middle path. Officers continue their civilian careers, serve each month, remain ready to deploy and keep a primary home base.
More Information
Consult Army Human Resources Command and GoArmy, then confirm current requirements and available routes with your recruiter before deciding.
- OCS candidates: prepare for GT 110 with our ASVAB for OCS study guide
Explore more Army medical officer careers. Start with the Medical Corps Officer and the Army Nurse Corps Officer. The four SP sections have their own pages. Read the occupational therapist, physical therapist, dietitian, and physician assistant profiles.